
Every year we receive a number of enquiries from people with Lyme disease looking for information and support. It is common for patients to experience delayed diagnosis and issues when accessing treatment. The following patient case studies illustrate common roadblocks that may prevent a timely diagnosis and adequate medical care.
Case Study 1: Lesley, 28 weeks pregnant, Scotland - July 2024
Scenario:
Lesley received a tick bite whilst pregnant and exhibited signs and symptoms of Lyme disease. These were not recognised by medical practitioners for weeks, resulting in delayed treatment. Testing for Lyme disease was undertaken too early in the course of disease to ensure accuracy and provided a false negative result.

7 July 2024: I found a tiny tick (lavae or nymph) embedded in my arm. It was removed within five hours with a tick remover tool. It was quite difficult to get out as it was very small.
2 weeks later: I was experiencing blurred vision and a headache. Paracetamol helped, but a week of a bad cold followed.
3 weeks post-bite: A rash appeared. It looked like an allergic reaction to a mosquito bite - red, circular and palpable.
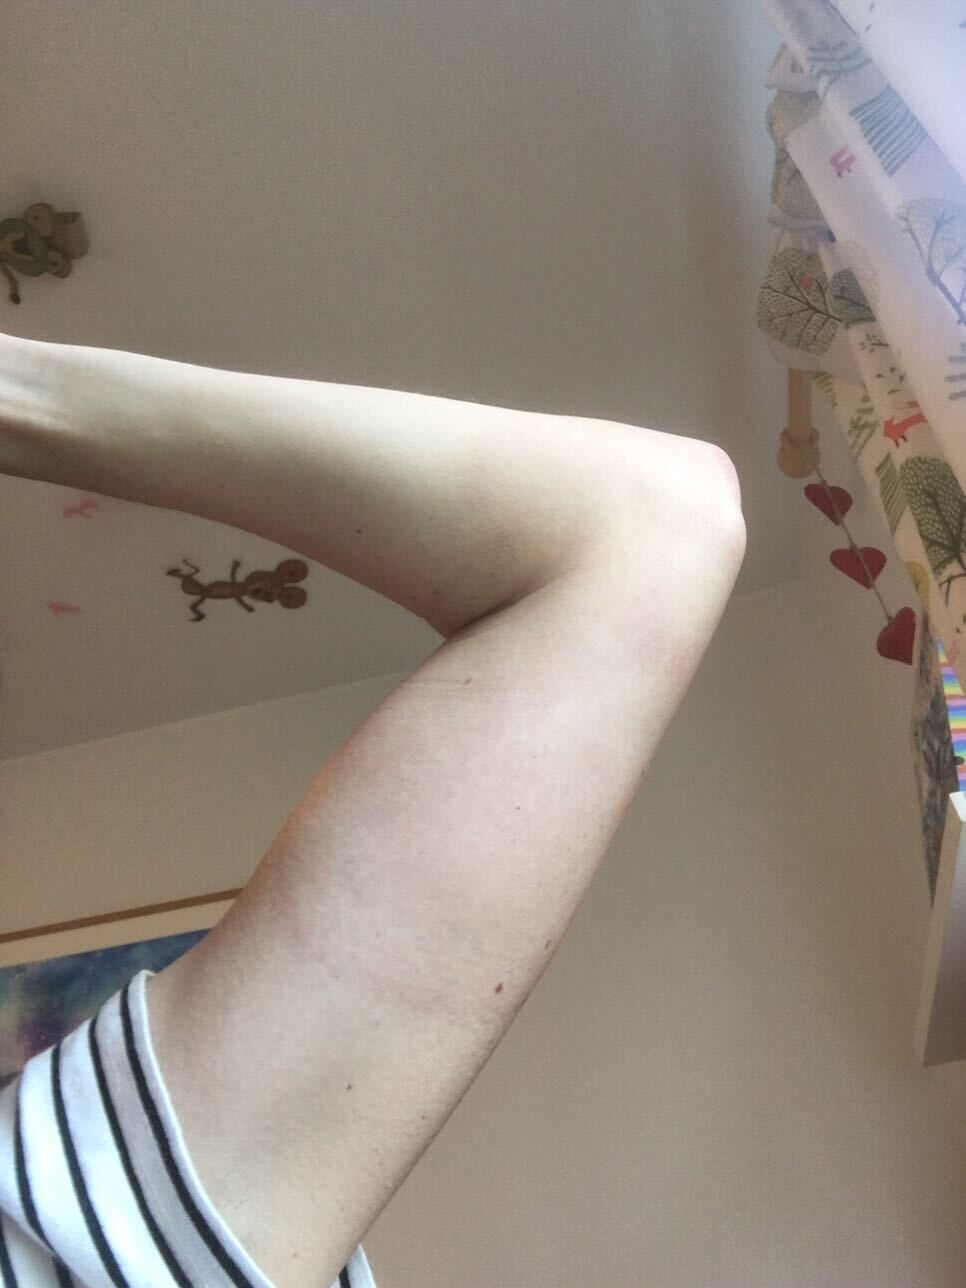
Four weeks post-bite: A spreading rash with a demarcated line developed. I went to my GP who did a blood test but the result was negative. The rash was not a typically round shape, but it continued to spread over 8 weeks. It was not hot, itchy nor painful.

Five weeks post-bite: I went to the pharmacy and was told to use moisturiser on the rash as my negative blood test had ruled out Lyme disease. The rash was still spreading, red, oval in shape and over 20cm in diameter. It was now turning a bit blue, but with a visible red mark at the initial bite location.
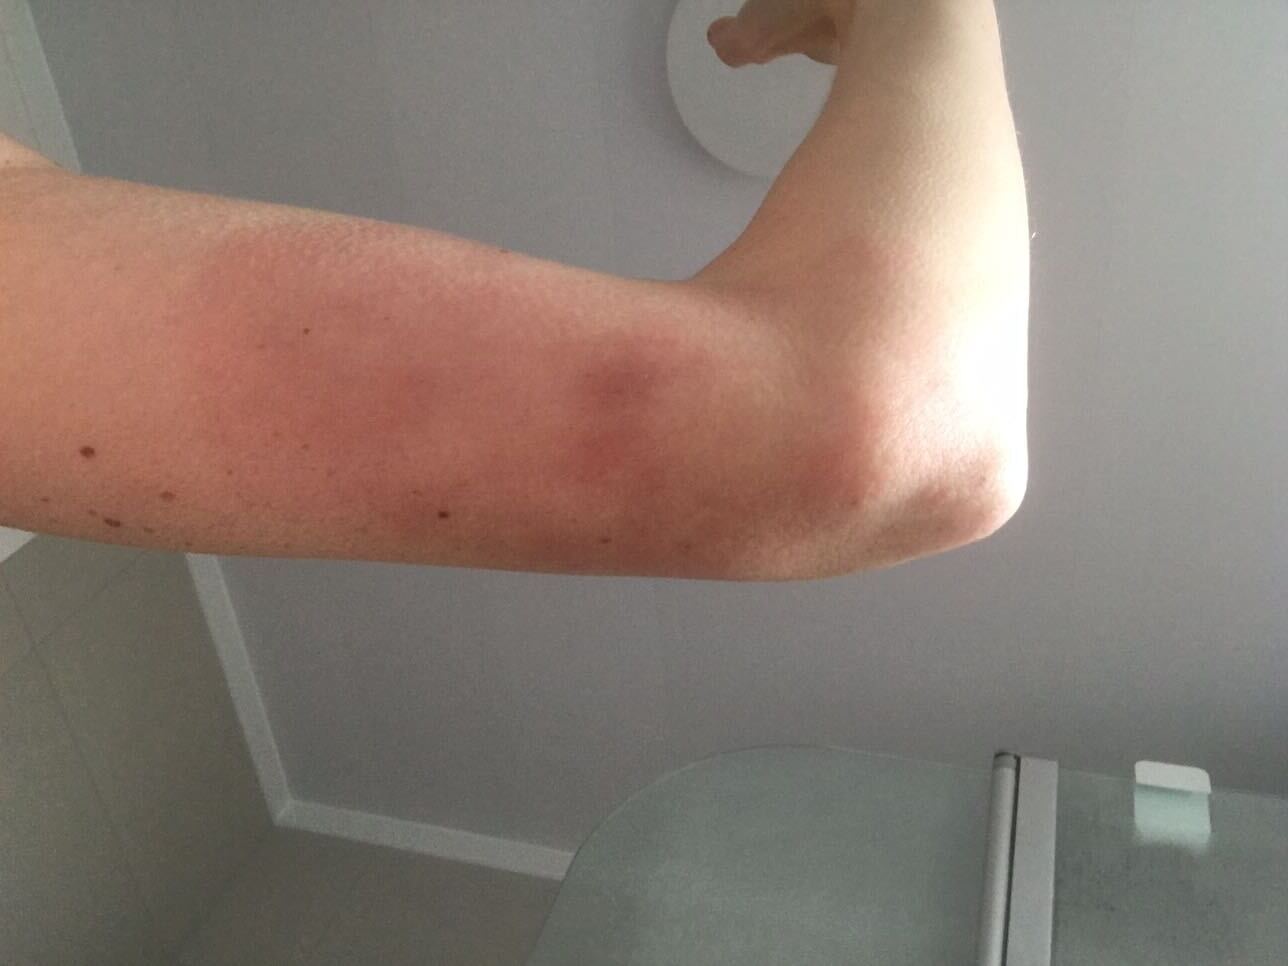
I went back to the GP, had a telephone consultation, emailed photos of the rash and was prescribed a steroid cream. I was told that it was not a typical bull's-eye rash so I would not be given antibiotics.
Six weeks post-bite: I called my GP again as the rash was spreading further and was told that a blood test could not be repeated until 10 weeks had passed since the first test. However I was offered a face-to-face appointment with a different GP at the surgery, who was a specialist in skin conditions.
He immediately diagnosed me with Lyme disease after looking at the photos I had taken of the rash to track its growth. I have not had any other symptoms.
As I was 28 weeks pregnant I was prescribed 1g Amoxicillin, 3 times a day for 21 days.
Eleven weeks post-bite: The GP did another blood sample. The rash stopped spreading and remained a little itchy, although not severely so and was treated with a skin cream.
Learning points:
- The patient experienced delayed diagnosis and treatment. It is essential to diagnose and treat as soon as possible, particularly if the patient is pregnant. Delayed diagnosis can allow the disease to spread throughout the body and increases the risk of long-term, difficult to treat complications.
- The presentation of an erythema migrans (EM) rash was not recognised by the GP. An EM rash is diagnostic of Lyme disease without the need of a blood test.
- Testing was undertaken too early to ensure accuracy. Antibody tests may appear falsely negative within the first few weeks of infection.
- The pharmacy team did not recognise the EM rash. The Pharmacy First pathway should ensure a patient with a tick bite or EM rash is sent to their GP, but this did not occur.
Case Study 2: Child with infected tick bite and facial palsy - March 2024
Scenario:
Erythema migrans (EM) rash misdiagnosed as ringworm. The doctor prescribed too low a dose of Amoxicillin for the child's age (375 mg, 3 x daily instead of 1g, 3 x daily) and she went on to develop facial palsy. Her mum only realised the dosage error after reading the children's facial palsy information on the LDUK website.

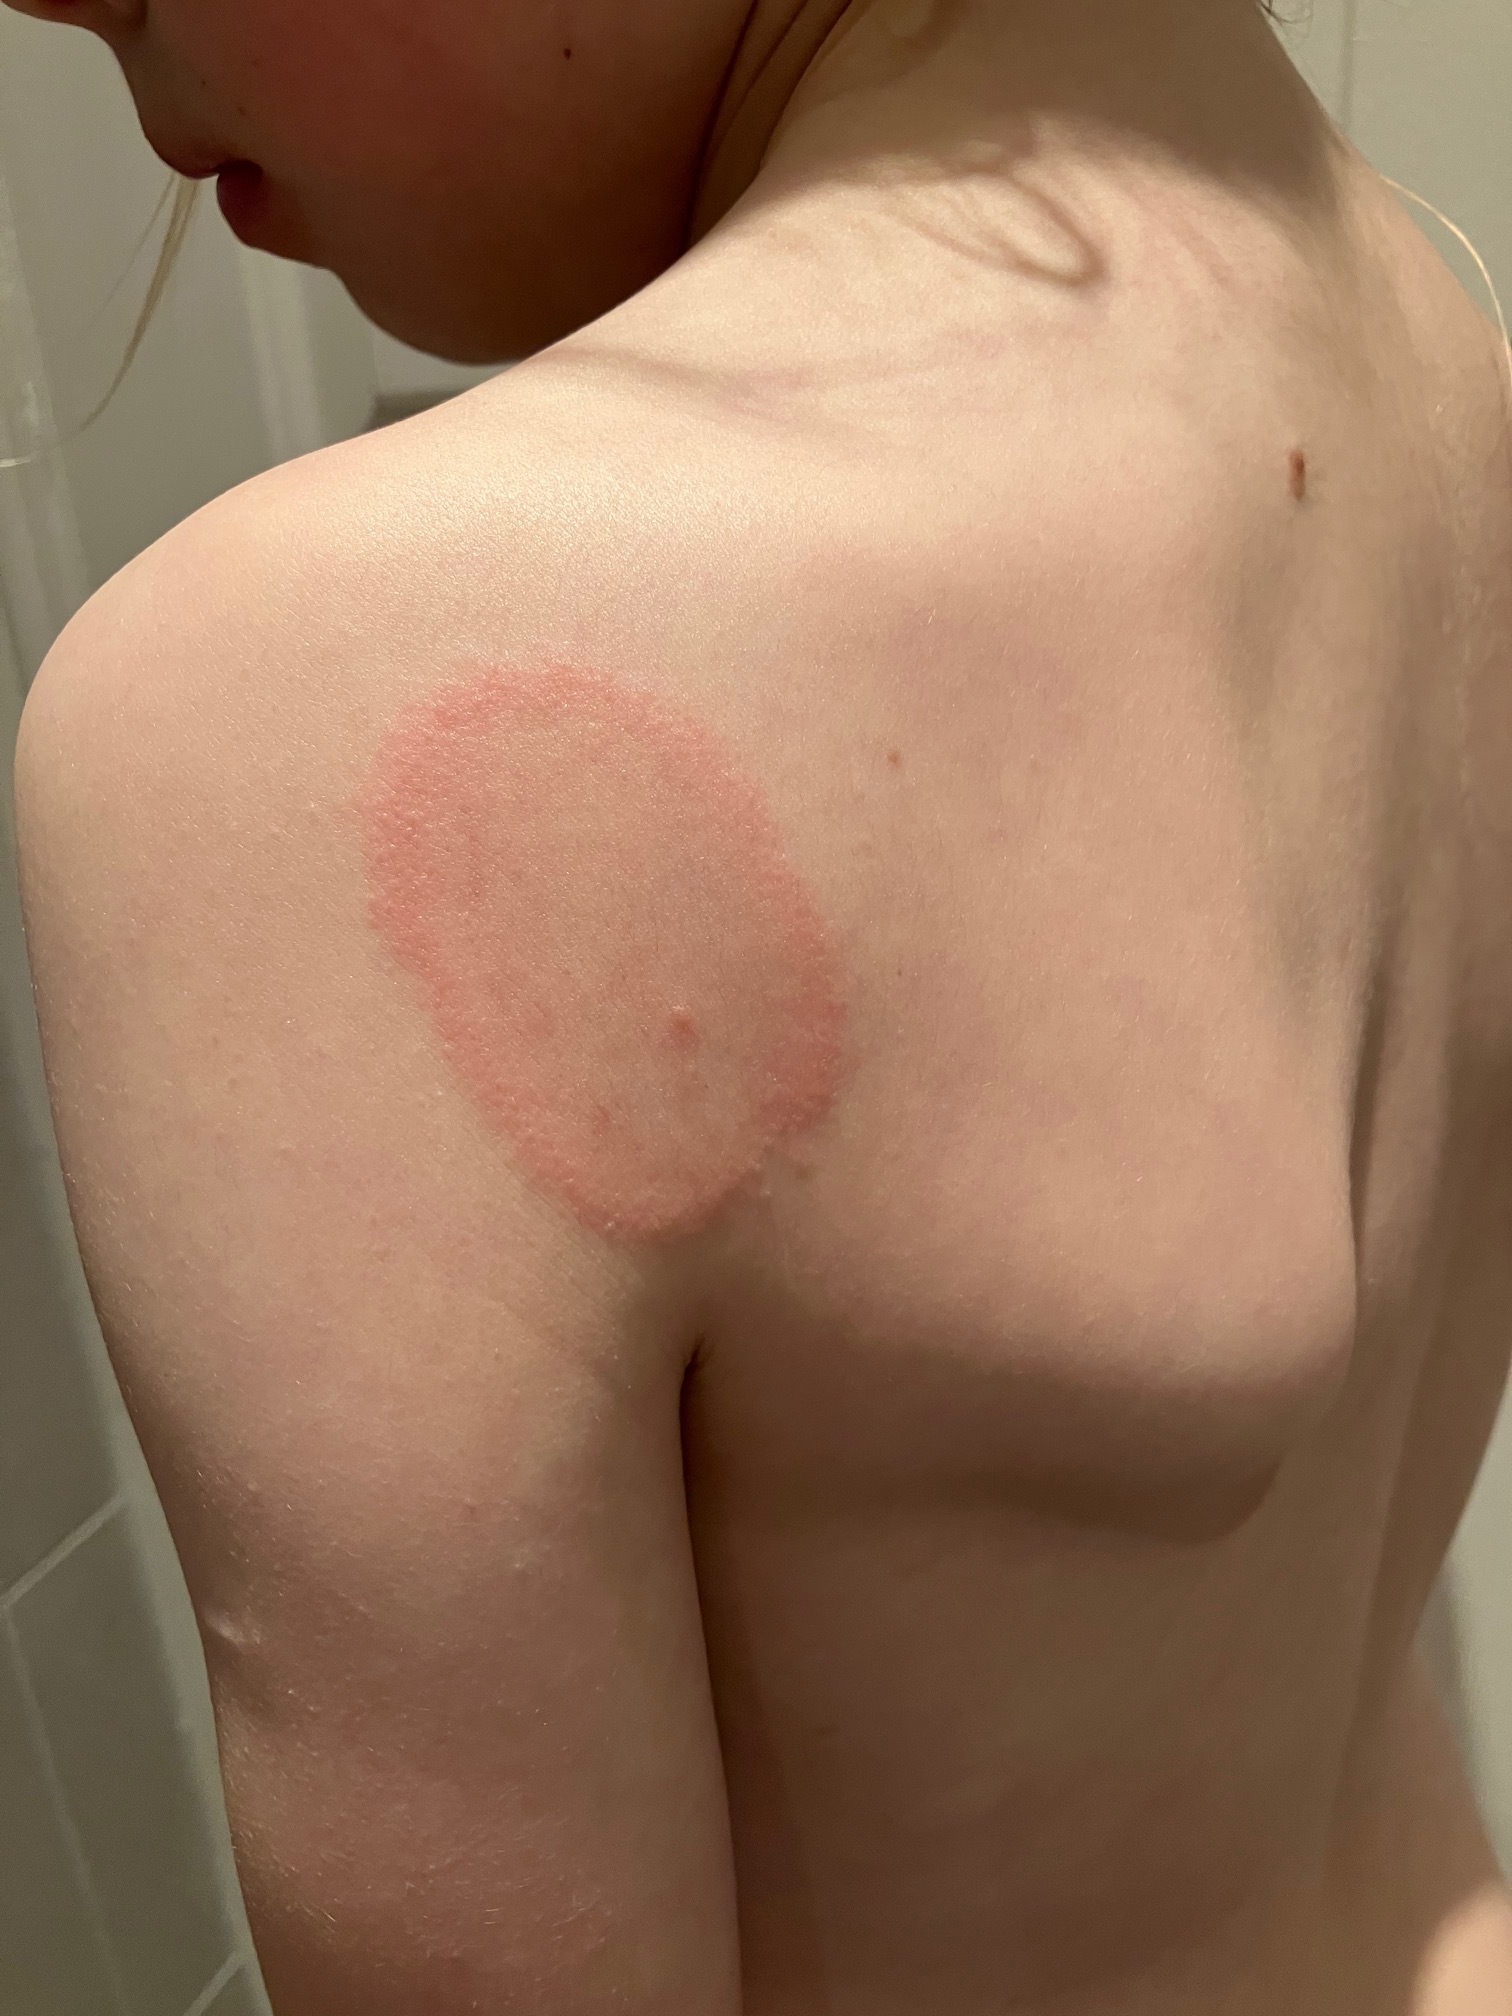

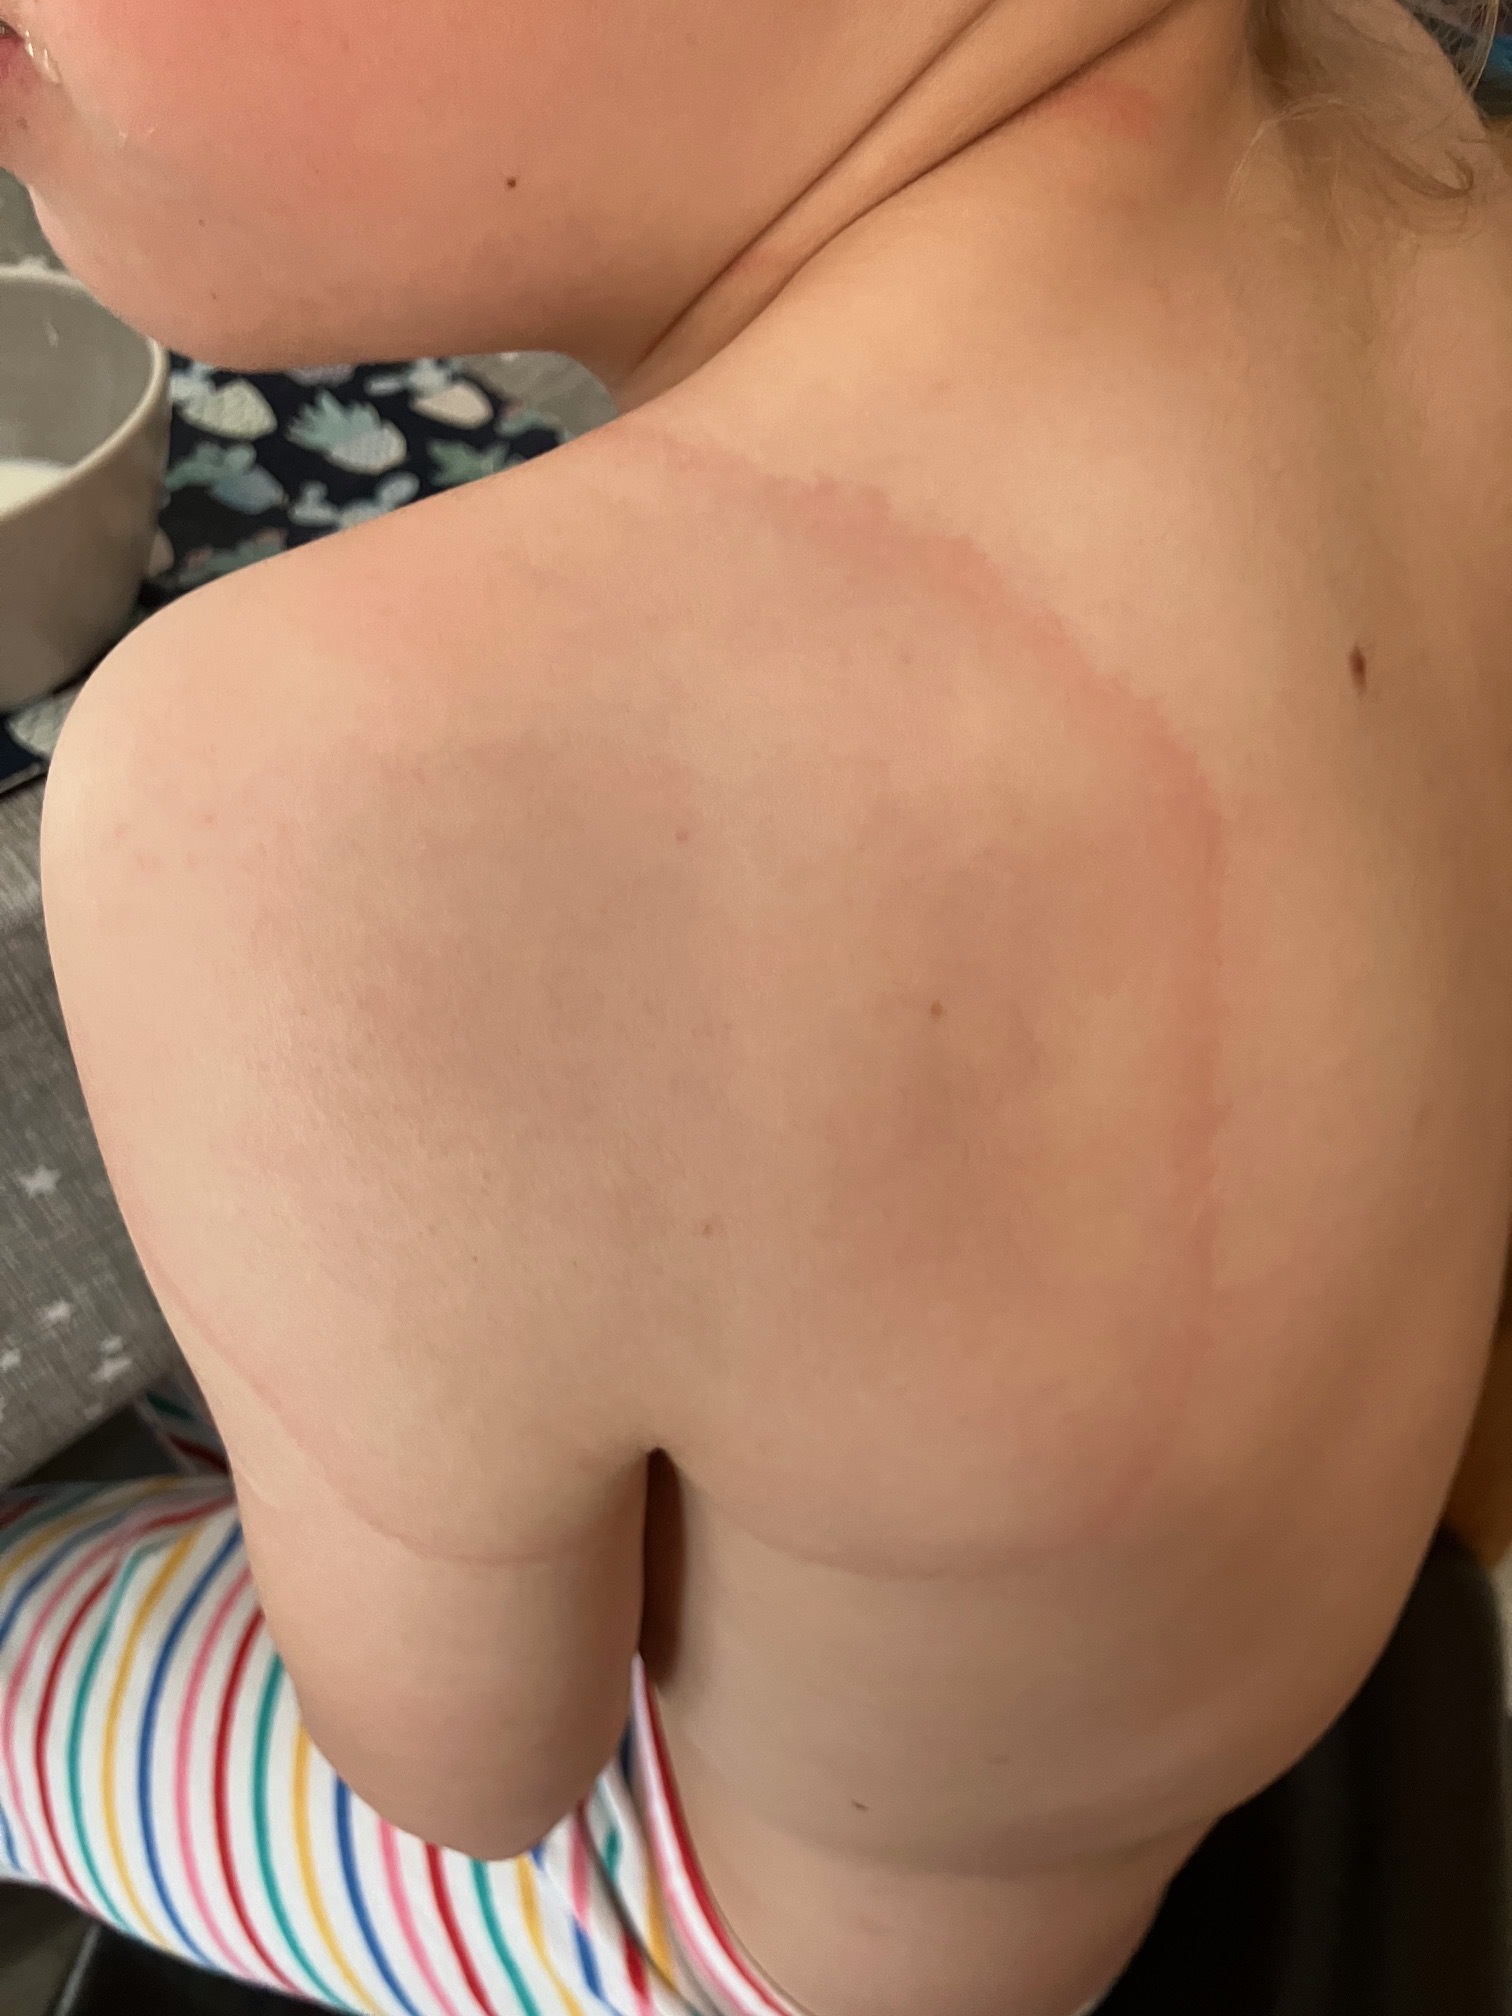
- Delayed diagnosis due to misdiagnosis of ringworm.
- Underdosing of antibiotics (dosage for Lyme disease is much higher than
for other childhood infections). - Lyme disease is the most common cause of facial nerve paralysis in children.
Case Study 3: Adult bitten in back garden, Leatherhead - August 2023
"I was bitten by a tick in our garden in August 2023, in Leatherhead, Surrey. Subsequently I developed an erythema migrans (EM) rash. 31st August doctors appointment - the doctor suspected Lyme disease, ordered blood tests and prescribed a dosage of Doxycycline which equated to less than 20% of the NICE guideline dose.
4th September - blood tests taken. I chased results without success, then received a text message from my doctor's surgery requesting I make a routine appointment, specifically noting it was nothing to worry about. Due to this being a routine appointment, it wasn't booked until 31st October. I was given a positive diagnosis of Lyme disease during this telephone appointment.
The doctor who took the appointment said the doctor who reviewed my test results had made a mistake not informing me sooner. As a result I have made a complaint and await a response.
I was prescribed the correct dosage of Doxycycline. This didn't help symptoms of chronic fatigue and neck pain, so I was also then prescribed a course of Amoxicillin as per the NICE guidelines following the Doxycycline. My symptoms of fatigue and neck pain have been ongoing since.
I changed surgeries and was then referred to St George’s Hospital, Infectious Diseases Department. They carried out a number of blood tests looking for other reasons for my symptoms, which all came back negative. They told me my ongoing symptoms have nothing to do with Lyme disease as the course of Doxycycline would've killed the bacteria and as I have negative test results discharged me back to my GP. I feel very let down as a result."
Learning points:
- Delayed diagnosis.
- Presentation of EM rash not recognised.
- An EM rash is diagnostic of Lyme disease without the need for a blood test.
- A negative Lyme disease test is not proof of cure or absence of the disease in cases of high clinical suspicion.
Case Study 4: Christine Kahan, bitten at picnic/in woodland - May 2024
"9th June 2024: Discovered insect bite on back of thigh and photo taken of bite site. Left it to go down, not thinking it could be a tick bite as no typical bull's-eye rash. Probable date of bite - 9th May 2024 whilst having a picnic and went into woodland.
18th June 2024: Found a live tick inside leggings which I recovered and put in a small tub. My dog had a vet appointment so I took it with me and the vet confirmed it was a tick.
21st June 2024: Submitted to triage for a GP appointment to discuss bite. Received text back from triage to see the pharmacist regarding the bite.
25th June 2024: Pharmacist advised to buy hydrocortisone cream for the rash but did not advise on other treatment for Lyme disease. I used the cream as directed.
1st July 2024: Submitted triage to GP requesting an appointment to discuss Lyme disease. Appointment arranged for 23rd July with GP.
23rd July: Discussed my symptoms and concerns about Lyme disease with GP and was asked what I would like to happen. I requested Doxycycline to be prescribed as per the NICE Lyme disease guideline. Due to the delay getting to see a doctor, by this time I had experienced very convincing Lyme symptoms over the previous weeks.
- Muscle and hip pain which meant I had to go upstairs one step at a time.
- General lower back pain
- Several episodes of excruciating vice-like pains in my head, neck and shoulders lasting 2-3 days each, plus a very painful, stiff neck.
- Shivers.
- Needed codeine to provide pain relief as paracetamol did not work.
- After each episode of head, neck and shoulder pain I felt generally ok again. GP thought that the hip pain may be arthritis. However, I now know that Lyme disease can affect joints and give pain and Lyme arthritis.
- Eyeball pain, either in one or both at the same time. Very severe pain which I associated with dry eyes but this could be a Lyme disease symptom. I bought eye drops for severe dry eye but the pain continued. Due to have annual eye test on 28th August so will discuss with optician also.
- Light and noise sensitivity.
- Tinnitus increased significantly in right ear. Initially I did not associate these symptoms with Lyme until the third occasion of head, neck and shoulder pains when I then began thinking about the possibility of Lyme.
- Return of head, neck and shoulder pains
- Raised temperature of 37.5 degrees C and night sweats. I had to sleep on a towel as the night sweats were so bad.
- My back felt like 'jelly' and had no strength. Could not sit up or get out of bed without help.
- Brain fog.
- Feeling dreadful and very ill.
- Strong tingling sensation down the inside of my right arm and into the 4th and 5th finger on 3 separate occasions.
- Extreme nausea for several days before I started on Doxycycline for Lyme disease on 31st July."
Learning Points:
- Triage at GP's surgery did not identify risk of Lyme disease and referred to pharmacy instead.
- Pharmacy did not identify risk of Lyme disease and did not urgently refer back to GP.
- 3 week delay until follow-up GP appointment despite patient's concern about Lyme disease. Patient should have been treated as an urgent case.
- Further delay of 5 days after the follow-up GP appointment before patient started Doxycycline despite escalating symptoms.
- Patients should be treated with urgency for Lyme disease where suspicion exists. The illness can be hard to treat at later stages, with complications and uncertain outcomes. Doctors should not wait for a Lyme disease test result, which can also give false negatives in some cases, especially in early disease.
Case Study 5: Child (male, age 9), bitten in West Yorkshire - October 2024
Scenario: A 9-year-old boy developed a distinct bull's-eye rash around a bite site after feeling unwell for a few days the week before. It was suspected the bite had occurred 1-3 weeks earlier. He had played in woodland at school (Forest School) and also regularly walked the dog in an area that could contain ticks.
Monday 14th Oct: The family could not get a GP appointment. The GP's receptionist advised over the telephone that the rash was likely ringworm and to buy appropriate cream. As the family were concerned the child was taken to the GP's surgery, but was not seen by a GP.
The pharmacist next door confirmed it was a bull's-eye rash from a tick bite and that cream would not help. He referred them urgently back to their GP's surgery. Again they were not able to see a doctor but it was suggested they email a photo of the rash instead, in order to hopefully obtain a telephone appointment.
The family decided to take the boy to A&E in Halifax. They saw a nurse or junior doctor (not sure which) very briefly as it was very busy. They were told it was probably ringworm and to try some cream for that.
Tuesday 15th October: The family called the hospital pharmacy about the cream prescription to see if this could be sent to a local pharmacy. After mentioning their concerns, this pharmacist also suspected Lyme disease and quickly referred them back to the GP. The family could not get an appointment.
Wednesday 16th October: NHS 111 referred the family back to hospital (Local Care Direct). Here they saw a more experienced doctor face-to-face who prescribed liquid Amoxicillin for 3 weeks for suspected Lyme disease.
The liquid Amoxicillin was not available from the late night pharmacy so the family were given large capsules instead. It was then noted that the prescription was only for a 2 week course of Amoxicillin, not the correct 3 week course the doctor had verbally recommended. The dosage given was also incorrect.
Thursday 17th October: The child was not able to swallow any of the capsules (he is on the autism spectrum). The family could not get a GP appointment, so NHS 111 sent them back to hospital for the liquid Amoxicillin prescription from a doctor.
The NHS 111 service requires the patient to be present at the time of the call. As the child travels to a special school in another county and would not return until after 4.30pm, the referral was delayed until the following day.
The family sought advice from LDUK. Understandably they were stressed and worried about being able to get a face-to-face appointment with a doctor and the correct dose of liquid medication quickly. Unfortunately it took until Tuesday 22nd October for the child to receive the correct treatment.
Learning points:
- GP's surgery incorrectly sent the patient to the pharmacist. The pharmacist fortunately knew tick bites are not covered by the Pharmacy First clinical pathway and rightly sent the patient quickly back to the GP.
- When finally seen at A&E, the bull's-eye rash (EM rash diagnostic for Lyme disease) was misdiagnosed as ringworm.
- When antibiotics were finally prescribed the wrong dosage was given (half the recommended dose for child's weight), for the wrong duration (2 weeks instead of 3), and the child was given tablets that he couldn't easily swallow (he has special needs).
- There were multiple delays in getting the appropriate treatment which was not given to the child until 22nd October. Correct antibiotic treatment must be given as early as possible in order to prevent possible complications.
Case Study 6: Kay Hayden, bitten inside her home in Lincoln - June 2024
Scenario:
Kay Hayden was bitten by a deer tick on her right shoulder, whilst lying on the sofa at home. She assumed the tick had been carried into the home on the cat, despite the cat having previously received preventative flea and tick treatment. There are allotments behind the house and deer are often seen in her garden.

17th June 2024: Kay felt and saw her tick bite. In her case it was painful and felt similar to a wasp sting. As ticks can be very small and their bite is often painless, many people do not notice or feel a tick bite at all. Kay's husband safely removed the tick but a slight rash appeared at the bite site over the following week.
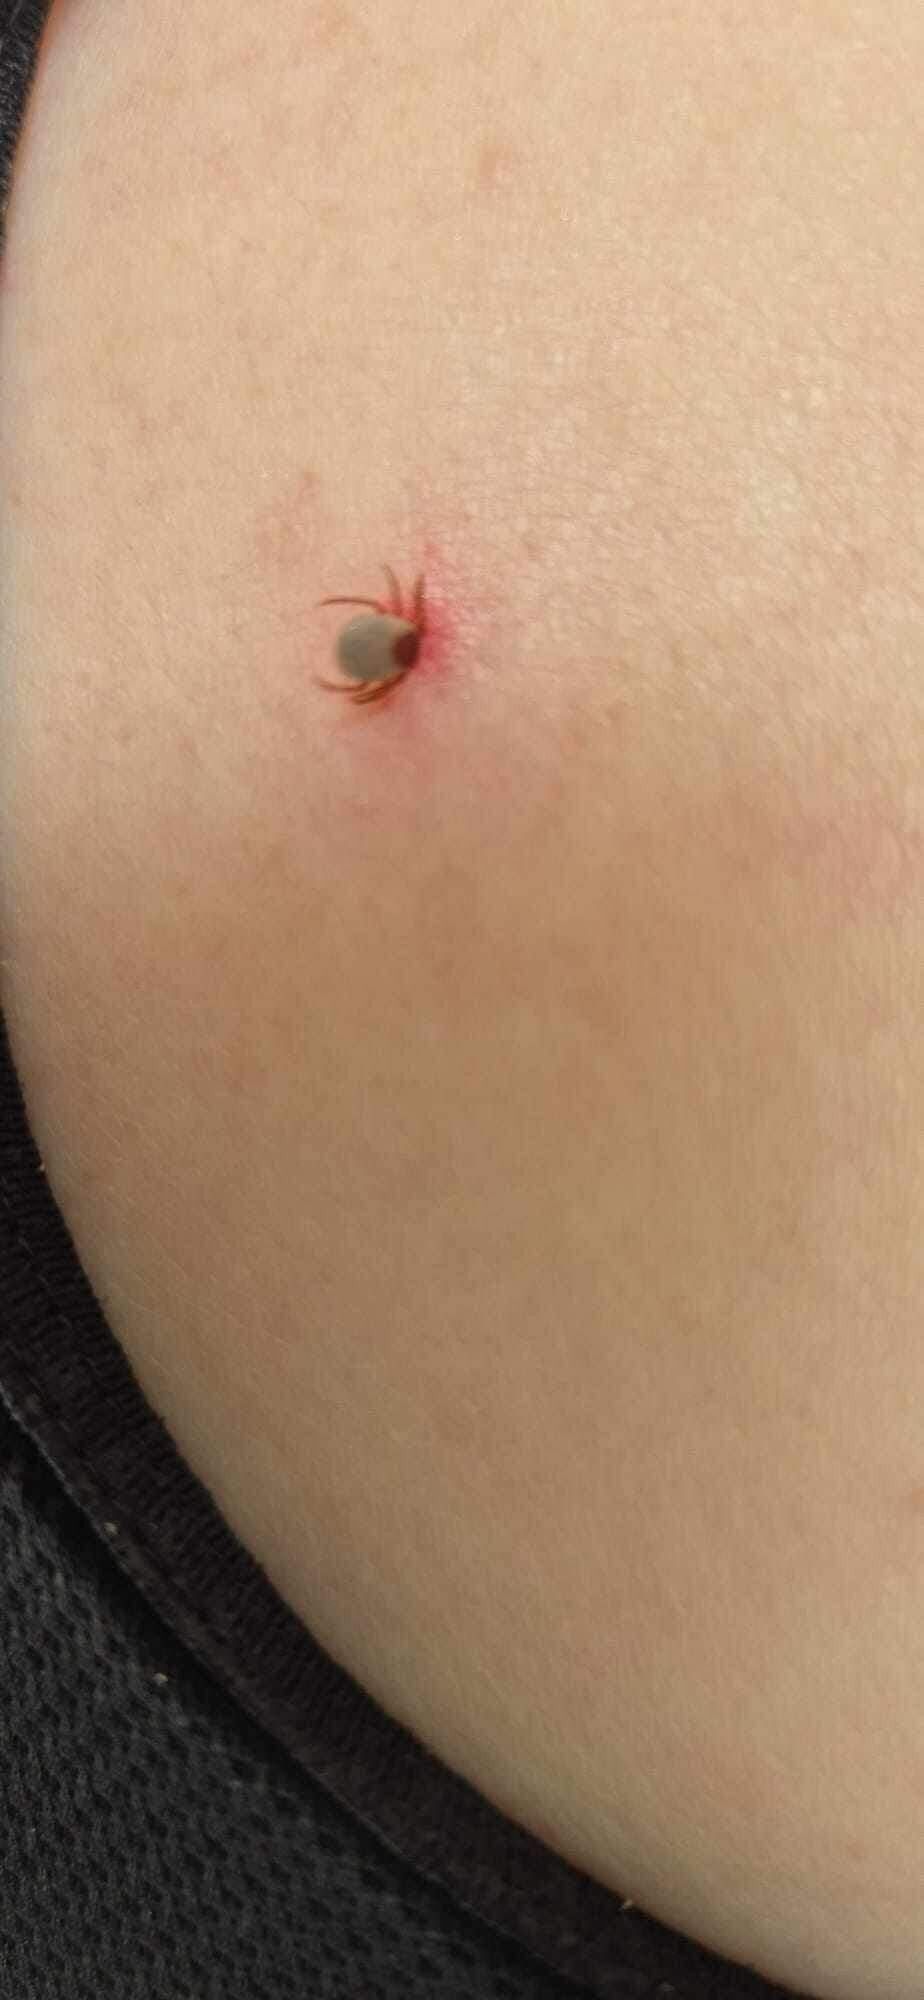
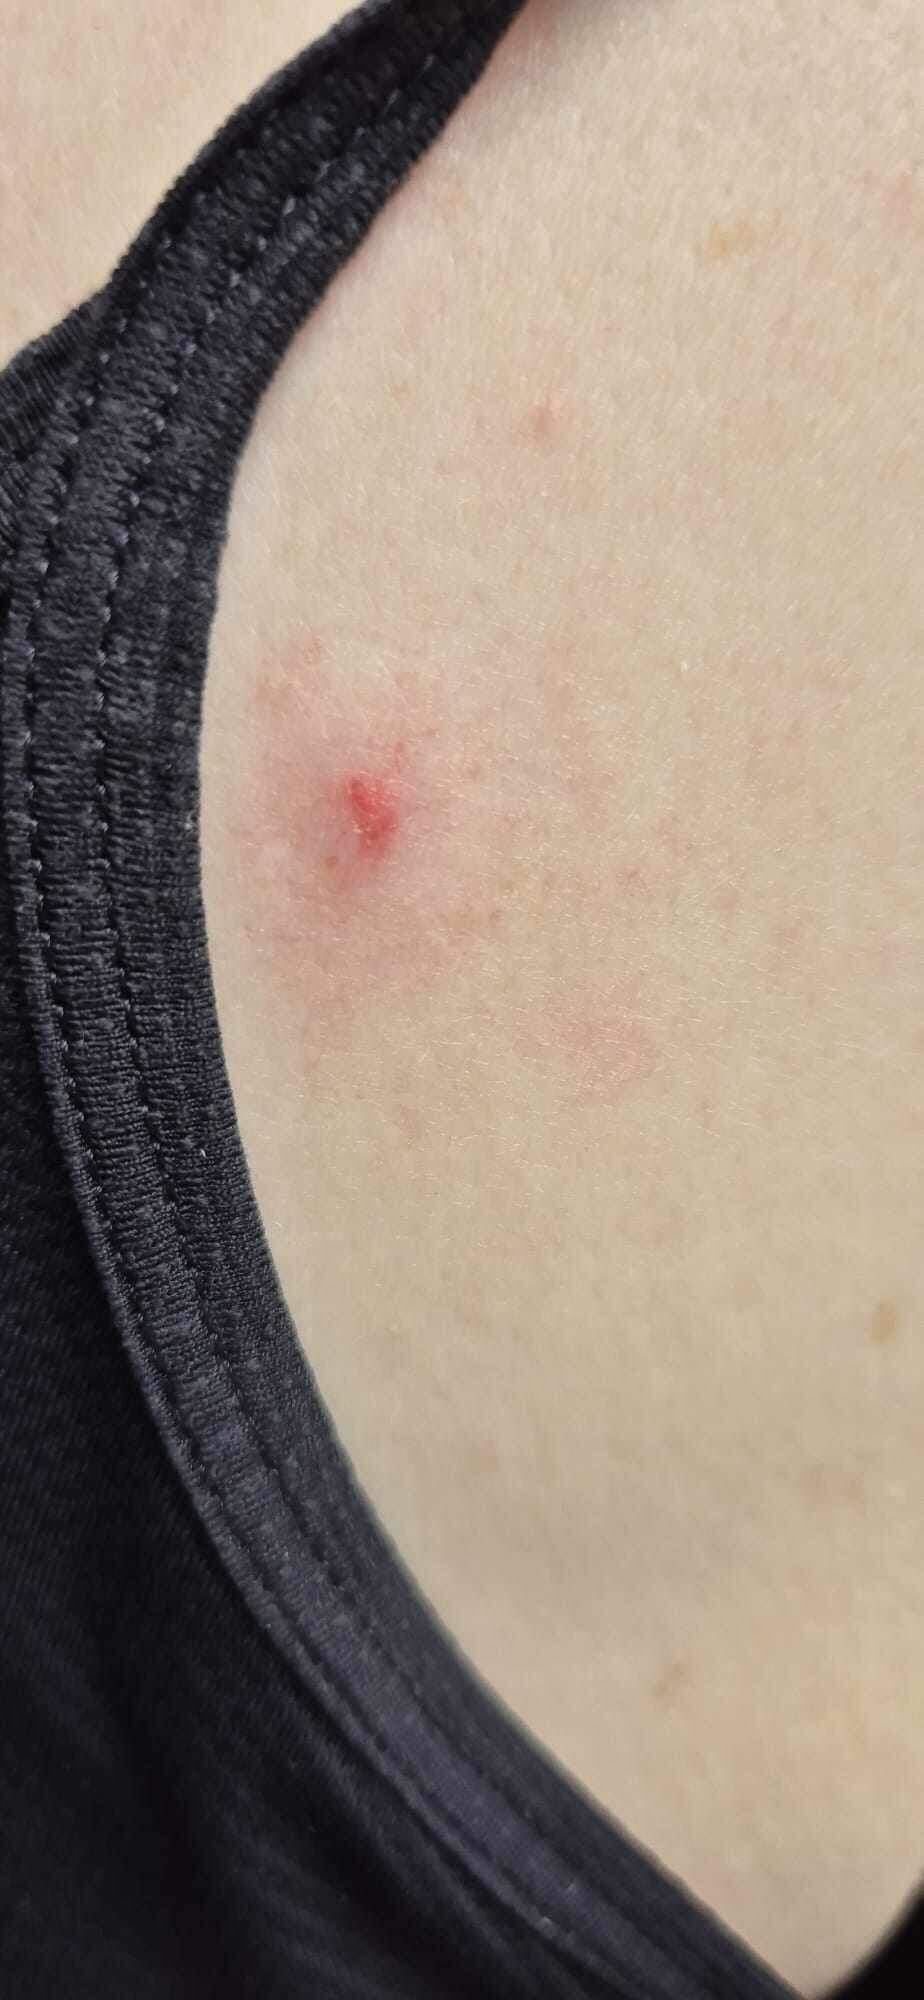
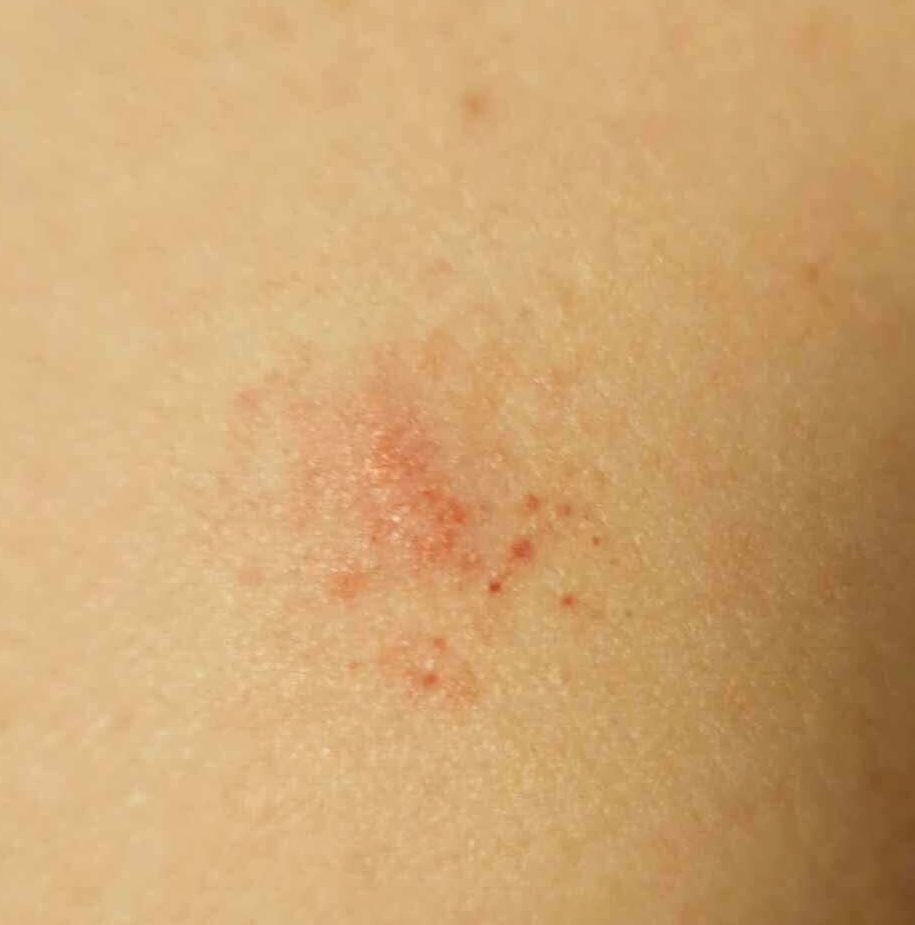
24th June 2024: Kay saw her GP and was prescribed Flucloxacillin 500mg 4 times/day (28 capsules). Unfortunately this is not the recommended first-line treatment for Lyme disease.
Over the next week she developed severe flu-like symptoms, chills, fever, head pains and vomiting. The rash evolved into a larger, more obvious, expanding erythema migrans (EM) rash.
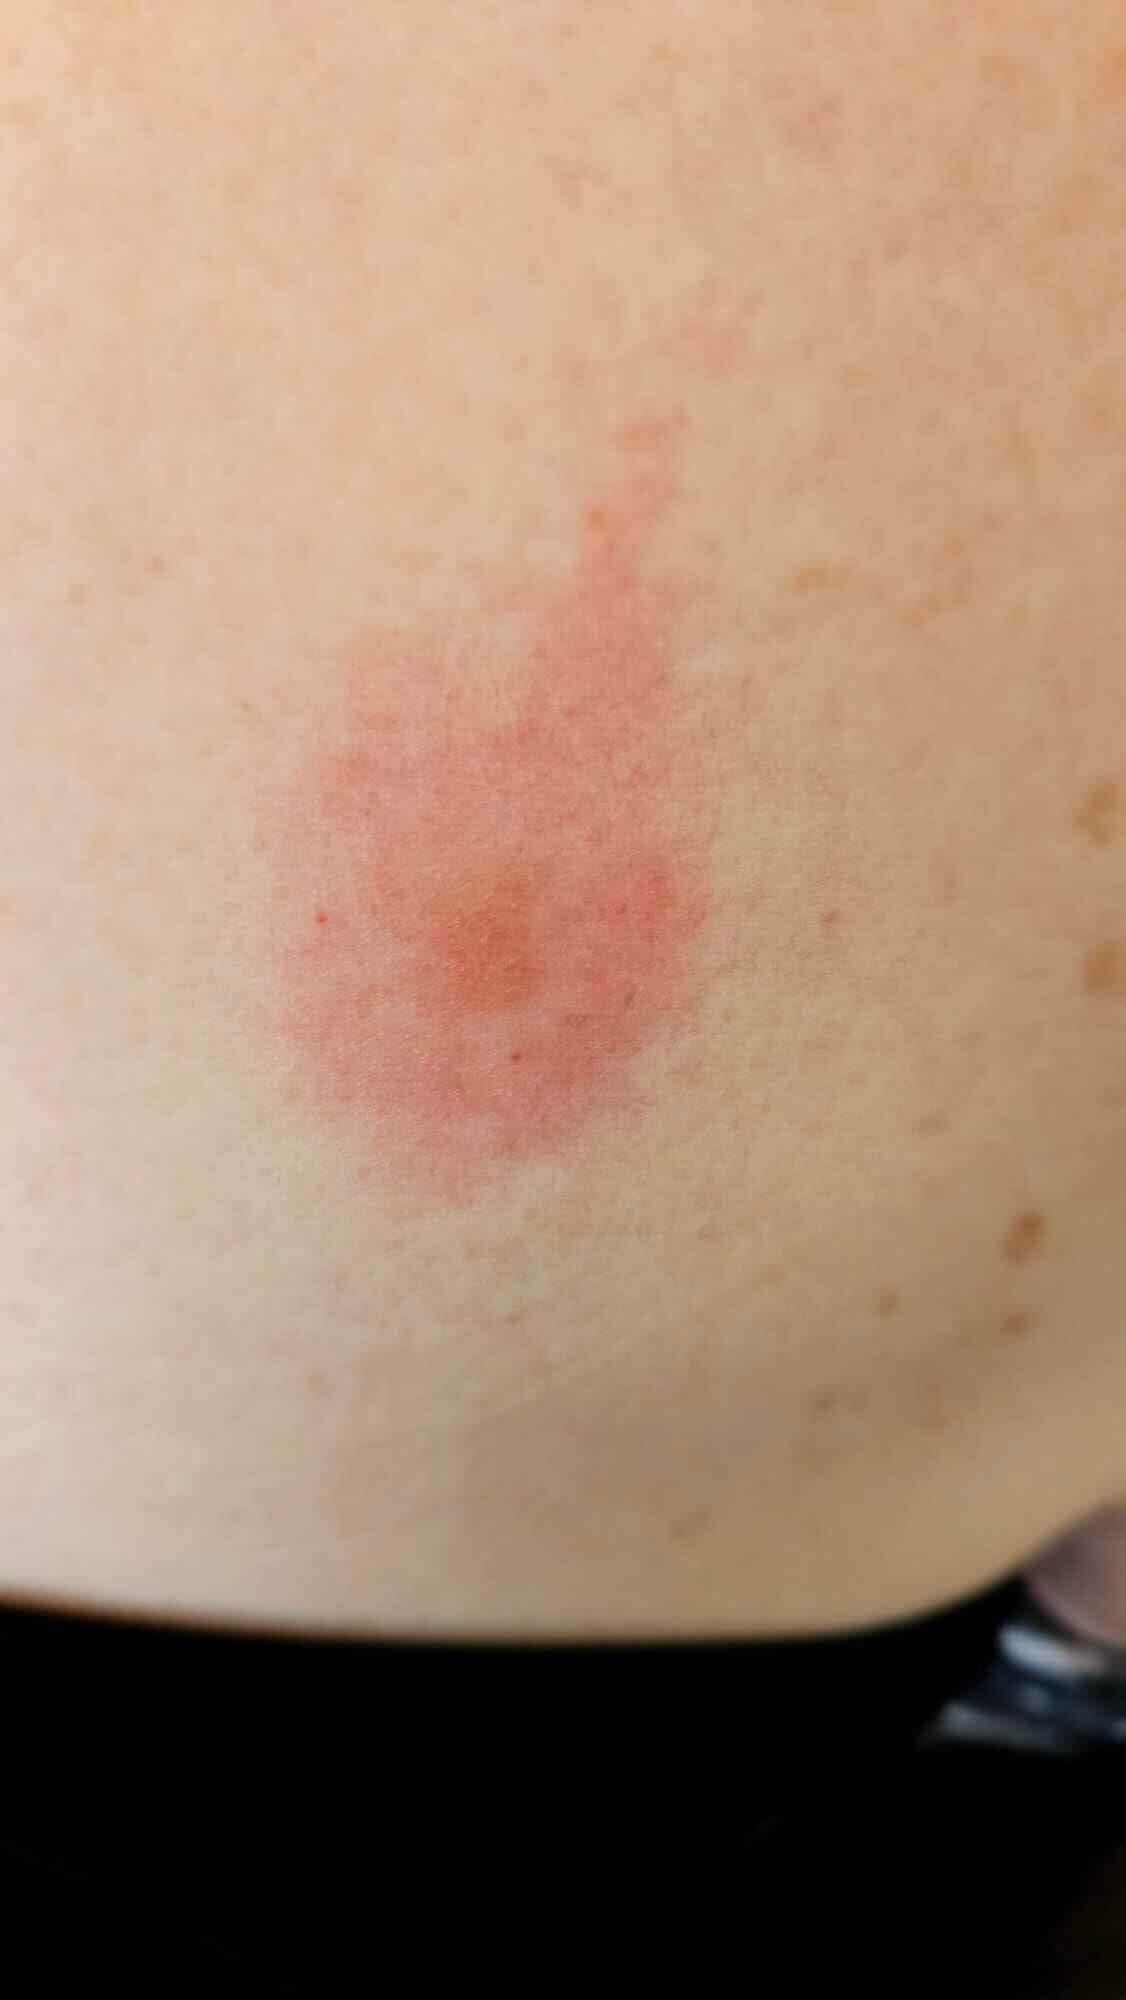
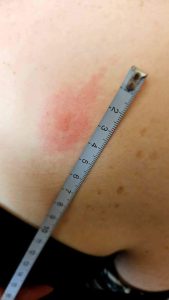
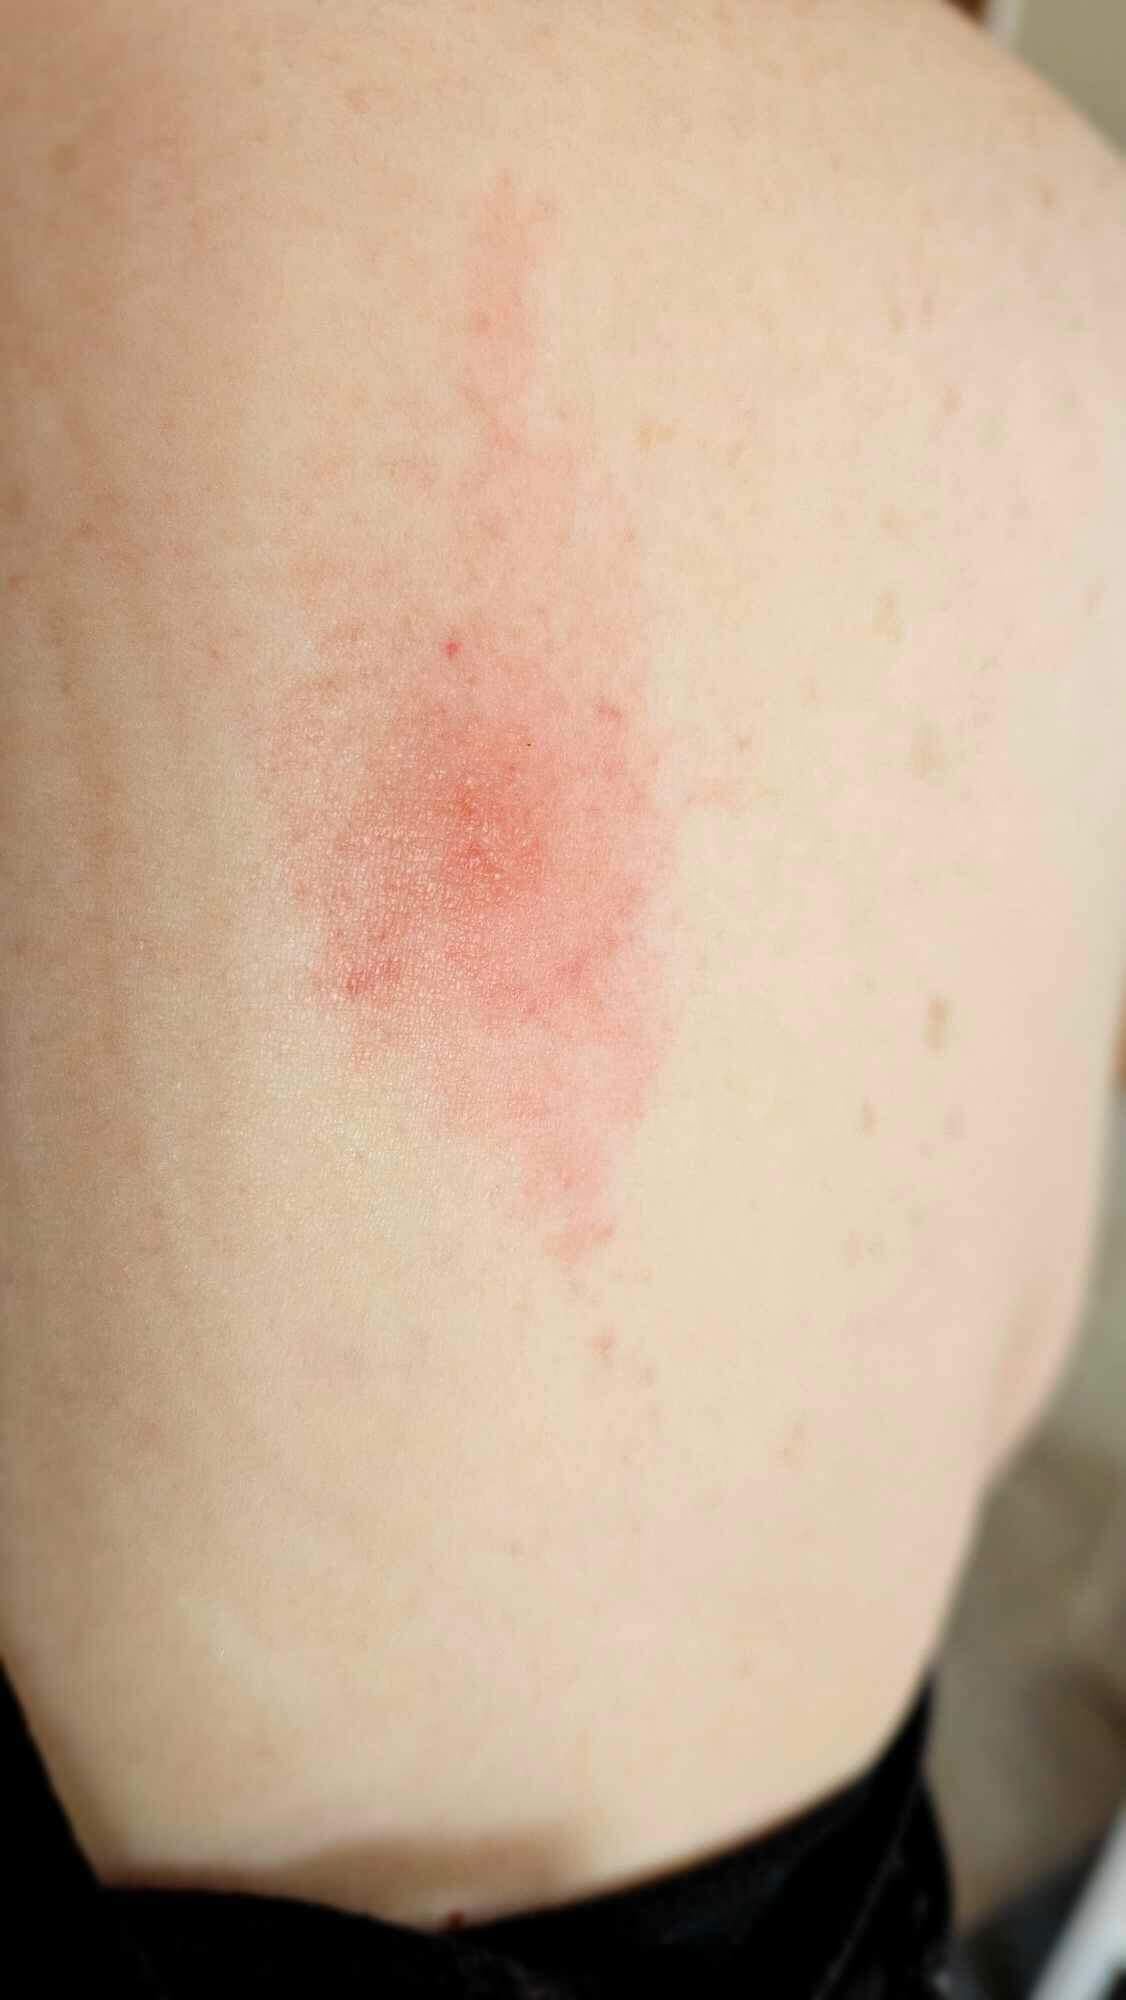
3rd July 2024: Kay sought further medical advice and was then diagnosed with Lyme disease. She was correctly prescribed Doxycycline 100mg twice/day for 21 days (42 capsules) to treat the infection, and also Cyclizine anti-sickness tablets, which worked well.
A couple of days into the treatment she developed a classic Jarisch-Herxheimer reaction but this settled relatively quickly.
Kay has been feeling well since completing her course of Doxycycline. Fortunately it appears that her treatment was prompt enough and sufficient enough in her case to be successful.
Learning points:
- Initially Kay's GP did not prescribe the correct first-line antibiotics for Lyme disease, likely because the diagnosis was uncertain at that stage. Lyme disease should be quickly considered following any tick bite.
- When appropriate treatment is delayed, complications can occur and a positive treatment outcome becomes uncertain.
- EM rashes do not always occur with Lyme disease. When they do occur they are diagnostic for the disease but may also be atypical in appearance, not always forming the expected bull's-eye shaped rash.
- Doctors should treat patients without waiting for a positive Lyme disease test result to confirm the diagnosis. Lyme disease testing currently has limitations. False negative test results may also occur early in the course of disease.
- Patients should be told to urgently return to their doctor for a second course of antibiotics quickly following the first, should any symptoms persist. They should also seek further medical advice for persisting or unexplained, new symptoms after this second treatment course is complete. Treatment failures are possible, particularly when a patient is not treated promptly following a tick bite.
Case Study 7: Chris Ward, East Devon - Early Summer 2024

24th August 2024 - Chris became bedridden with flu-like symptoms and pain. The aches and pains would flare then subside and he would feel normal again. Again symptoms were put down to stress.
Early October 2024 - Severe mobility issues and worsening pain drove Chris to A&E. Doctors noted some previous back pain and although different in nature, Chris was sent home with a diagnosis of sciatica and advice to take painkillers as necessary. Scans and blood tests in hospital were normal.
Mid October 2024 - Over the next 7 days the pain and ability to move his legs worsened. Chris could not climb the stairs. His sleep became so disrupted he was waking hourly. He returned to A&E. In hospital it was poor knee reflexes were discovered and Guillain-Barre Syndrome was suspected, an autoimmune disease. Chris was admitted to a neurological ward, underwent an MRI and more testing, and was treated with IVIg infusions unfortunately with no improvement in his symptoms.
As there was limited concrete evidence to support the suspicion of Guillain-Barre, a lumbar puncture was arranged to test for other neurological issues. This returned positive for Lyme disease and although symptoms were indicative it was a surprise as Chris had no memory of a tick bite or any rash. It was suspected that the norovirus infection in September could have escalated pre-existing Lyme disease.
Chris immediately received IV doxycycline for 5 days and then oral antibiotic treatment. By now in a wheelchair with considerable pain he was sent to a rehabilitation unit, where slowly his mobility has somewhat improved.

- Despite some typical early symptoms of Lyme disease, there was no known tick bite or bulls-eye rash to flag the infection and symptoms were put down to summer flu, stress and lifestyle factors.
- Early antibiotic treatment is critical to give the best chance of recovery.
- Sciatica then Guillain-Bare Syndrome were later suspected by hospital doctors as the infection spread throughout the body.
- Blood tests and scans did not reveal the infection.
- Luckily the lumber puncture led to the correct diagnosis however this is not always positive in cases of Lyme disease.
- As there is no test available to show when the infection has gone, there is uncertainty around appropriate future treatment. Ongoing antibiotic treatment may not be covered by the NHS.
- Due to a delayed diagnosis Chris continues to suffer neurological and mobility problems which greatly affect his life, with no idea if or when he will fully recover.
Case Study 8: Child (aged 5) with facial palsy following non specific symptoms
Scenario: A 5-year-old child presented with facial palsy following nonspecific symptoms, including lethargy and headache. The cause was later found to be Lyme disease despite no known tick bite or erythema migrans (EM) rash.
The child was diagnosed with lower motor neuron (LMN) palsy, with a neurological examination revealing no other abnormalities. The patient demonstrated persistent right-sided facial weakness, accompanied by complaints of headache and back pain. Clinical evaluation indicated marked right-sided facial motor weakness, characterized by an inability to raise the eyebrow, close the right eye, smile, or puff out the cheek. The remainder of the neurological assessment was unremarkable. There was no known tick exposure.
Given the persistence of symptoms six weeks after the initial diagnosis, a thorough investigation plan was implemented to exclude other potential causes of lower motor neuron (LMN) palsy. This plan included brain imaging, routine blood tests, and specific tests for cytomegalovirus (CMV), herpes simplex virus (HSV), and Lyme disease. Laboratory results revealed positive IgG and IgM antibodies to Borrelia antigen, indicating recent or active Lyme disease, while the remaining investigations returned normal findings. The patient was subsequently treated with a three-week course of oral amoxicillin, in accordance with NICE guidelines.
The patient‘s guardian reported substantial improvement in both facial paralysis and the overall clinical condition, with no significant concerns observed. The patient is currently under follow-up care with the general paediatric team.
Learning points:
- Lower motor neuron (LMN) palsy is an uncommon condition in children under the age of five, with Bell’s palsy being the most prevalent cause of isolated facial paralysis. Nevertheless, Lyme disease should be considered as a differential diagnosis, given the significance of early diagnosis and treatment, even in the absence of exposure to ticks or a known tick bite.
- Timely diagnosis and appropriate antibiotic therapy are essential for achieving optimal recovery, especially in paediatric patients, highlighting the need for increased awareness among healthcare providers.
- Multidisciplinary collaboration is essential for optimizing patient management and recovery.
Read more at:
Case Study 9: Tony Ford, bitten in the South West - Summer 2021
Scenario:
Tony Ford was bitten by a tick in the South West in the summer of 2021 and contracted Lyme disease. Although he was quickly diagnosed and received appropriate antibiotic treatment, the disease progressed to affect his heart.
Summer 2021
Tony suffered from initial flu-like symptoms, generally feeling unwell and unable to function for about 3 weeks. A large red erythema migrans (EM) rash appeared on his hip which he recognised was likely due to Lyme disease. He was seen by a GP within 2 hours and received about 2 months of antibiotics overall to treat the infection.
Although the flu-like symptoms cleared his memory remained poor and he struggled with even the lightest exercise. Normally fit, he found he could not longer easily walk upstairs without becoming out of breath. Chest pains began then in late November he was rushed into hospital where significant heart failure was found. It was concluded the bacteria had affected the heart muscle and nerves.
Tony received treatment and was monitored for several months however continued to feel tired all of the time and struggled to live his life. He had to leave his old job and his career suffered. Physical activity was risky and restricted.
Early 2024
Further investigations revealed that heart muscle function was declining more rapidly and Tony was fitted with a pacemaker and defibrillator which fortunately became a turning point.
The heart muscle mainly recovered and Tony felt loads better, fitter and energised. His memory has slowly recovered. However he still has to manage activity carefully, take medication and has a pacemaker for life.
Learning points:
- Tony received appropriate antibiotics swiftly only after he noticed the erythema migrans rash and suspected Lyme disease. He had flu-like symptoms and fatigue for 3 weeks prior and earlier antibiotics may have improved the outcome. Question patients about the potential risk of tick bites and Lyme disease should they present with flu-like symptoms, particularly in spring and summer months. Consider time spent in woodland and rural settings but also on golf courses, in parks, and urban gardens, as well as known Lyme hotspots.
- Educate patients about signs and symptoms of Lyme disease and the need for prompt medical care (consider displaying awareness materials for example).
- When Tony's medication ended he remained symptomatic with poor memory, breathlessness on exertion and inability to exercise as normal. This should have raised concerns around continuing infection/further damage and prompted intervention at this point. Optimum treatment for Lyme disease is yet to be confirmed and in some cases there may be need for prolonged treatment for the disease. Ensure patients know to return to their GP promptly for evaluation if any symptoms continue and monitor patients over time particularly where cardiac or neurological issues may be involved.
- Despite receiving hospital care Tony's heart function continued to worsen until he received a pacemaker and defibrillator in early 2024. Ensure patients are regularly monitored and the impact of Lyme disease and coinfections are ongoing considerations. It is not uncommon for patients to relapse.
Case Study 10: Tracey West, bitten in the South West in August
Scenario:
Tracey West experienced atypical erythema migrans (EM) rashes on her shoulder blade and from her spine around to her abdomen following an unknown tick bite. She did not receive a swift Lyme disease diagnosis or treatment allowing the infection to spread to the cerebrospinal fluid and brain.
Tracey's initial bite site presented as a huge lozenge-shaped bruise under her shoulder blade in August. She consulted a pharmacist when she noticed the initial rash and was given hydrocortisone cream as unfortunately the diagnosis was missed. She was advised to go to her local GP surgery after a week if the rash didn't resolve. Both her GP and practice nurse could not identify the rash at that point either but did photograph it for her records. Tracey was given another cream and asked to return in 10 days if it hadn't resolved.
The rash did not go and a further 2 prescriptions for different creams were issued again with no effect. After that Tracey was simply told to keep an eye on the rash and return if it caused further problems. At this point, she also noticed a leopard spot type rash on her abdomen, in addition to the ongoing rash under her shoulder blade. In following weeks the area around her rash started to go numb.
A few months later, Tracey experienced excruciating pain and numbness around to her belly button and electric shocks in her hands. In late November and early December she visited A&E and her GP again multiple times seeking a diagnosis, and drew the doctors' attention to the rashes.
Doctors misdiagnosed costochondritis, radiculopathy and pleurisy. Eventually a senior consultant at A&E admitted Tracey for a wider range of tests and connected her with a neurologist. Lyme disease was finally diagnosed via a lumbar puncture.
Learning points:
- Erythema migrans rashes can by atypical in appearance and do not always form a bull's-eye shape. They can present at the site of a tick bite or develop at other areas around the body.
- Consequently the pharmacist, GP and nurse did not recognise the rash or make the correct diagnosis early on in the course of the disease when it is easiest to treat. It was helpful however that the GP photographed the rash as a record.
- Hospital doctors did also not connect symptoms of numbness, severe pain and electric shock sensations in the hands to the rashes and the potential diagnosis of Lyme disease.
- Diagnosis came only after a lumbar puncture, once the infection had spread to the central nervous system. This was fortunate as a lumbar puncture result negative for Lyme disease does not necessarily rule out the infection.
- Late stage Lyme disease is more difficult to treat and can result in uncertain outcomes and ongoing ill health.
Case Study 11: Child (female) with facial palsy, likely bitten in France, 2025
Scenario:
Shortly after returning from a family holiday to France, Ella experienced early signs of facial palsy and was initially incorrectly diagnosed with a suspected unspecified allergic reaction by a doctor in A&E. As the facial palsy became more pronounced the next morning, Ella was again taken to A&E. The doctor there was aware that Lyme disease can cause facial palsy so tested Ella and a few days later results confirmed the diagnosis. Ella quickly received appropriate antibiotics and all symptoms resolved over the following weeks. This shows how important it is to consider Lyme disease in cases of facial palsy, and the value of early antibiotics to effectively treat the infection.

Ella's parents noticed something odd about their daughter’s eye shortly after returning from their holiday. It looked like she was squinting, and by the next day it had become really noticeable. She was holding her eye strangely and they were concerned enough to seek medical advice.
After calling 111 they visited A&E, where Ella was given Piriton for a suspected unspecified allergic reaction. After that, the eye seemed to improve, so they felt somewhat reassured.
However the next morning it was clear that Ella was squinting and one side of her face wasn’t moving at all. Her eye looked more open than usual because the muscles around it weren’t working.
The family attended Winchester A&E where Ella was diagnosed her with Bell’s palsy. The doctor there knew that facial palsy can be linked to Lyme disease so tested for the illness even in the absence of a known tick bite or a erythema migrans (EM) rash. Ella was given antibiotics straight away while waiting for blood test results to limit the spread of infection. She was also given a course of steroids to help with nerve inflammation.
A few days later, test results showed Ella was positive for Lyme disease. At this point she had no other symptoms - no fever, no rash, no joint pain - just the paralysis on one side of her face. Ella was also referred for an eye appointment as her eyelid wasn’t closing properly.
Three weeks later Ella's symptoms had completely recovered following her course of antibiotics. A quick diagnosis and early treatment had resulted in an excellent outcome.

Learning points:
- Early symptoms of facial paralysis were unclear and were not linked to Lyme disease by the A&E doctor.
- Fortunately Ella returned to A&E quickly as the facial paralysis became more obvious. The doctor was luckily aware of the link with Lyme disease, particularly in children, even without a known tick bite or EM rash.
- Appropriate antibiotic treatment was started quickly without waiting for Lyme disease test results. This is important as Lyme disease tests may not be accurate in early-stage disease. There are also other limitations with tests for Lyme disease so they cannot be used to rule out a Lyme infection where there is clinical suspicion of the illness.
- Early diagnosis and antibiotics are important to treat the illness and prevent later-stage disease.
Further information: