
My recent journey with Lyme disease began in summer 2025 after a tick bite. However, I have had a previous history of Lyme disease, which I also want to briefly share.

Maja Bagdziun
In 2015, during camping in Scotland, I was infested with ticks. I think I must have removed 8-10 ticks from different parts of my body. I never checked for rashes at that time, as I did not really have much knowledge about Lyme disease.
Over the following years, I developed a range of widespread symptoms which gradually affected my quality of life. In 2021, I underwent investigations for these symptoms and was diagnosed with fibromyalgia.
Around the same time as my fibromyalgia investigations, I experienced another tick exposure. I photographed the tick while it was still attached and documented the development of a spreading rash the following day. The appearance of the rash was considered clinically compatible with erythema migrans (EM), and I was treated with antibiotics.
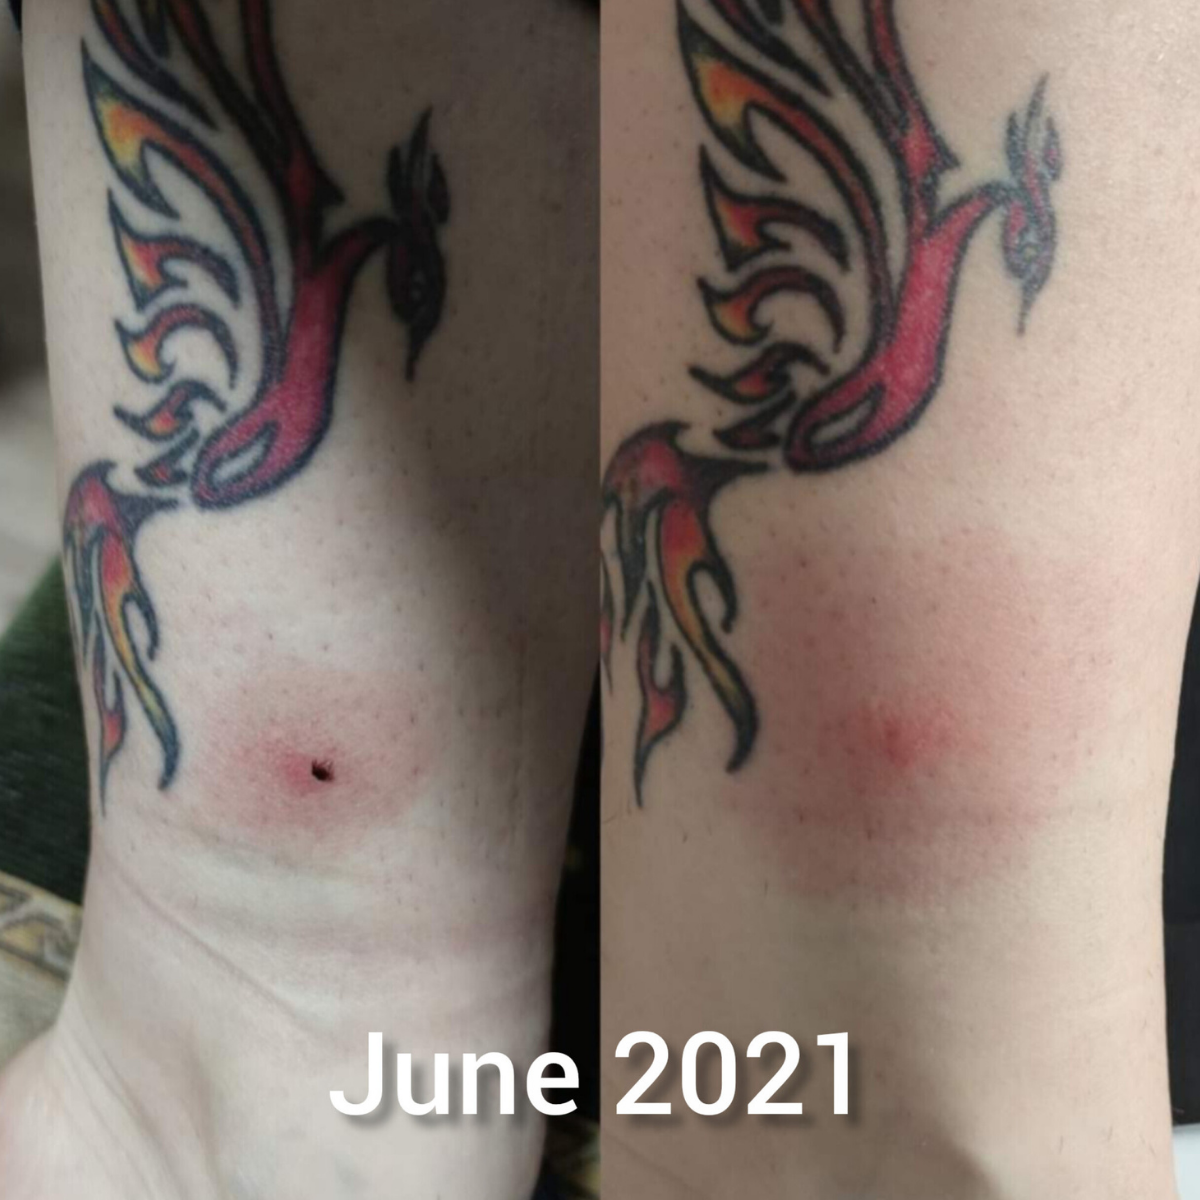
Maja’s 2021 tick bite and EM rash
Following this treatment, I noticed that my fibromyalgia-type symptoms gradually improved significantly over time. I cannot prove that there was a connection, and at the time I did not make any link between the two events, but it is something I have reflected on since my more recent illness began. I have wondered whether the antibiotic treatment may have played a role.
Another tick bite causes new symptoms
My more recent journey began in summer 2025 after another tick bite. On 6 June 2025, I was bitten by a tick on my left armpit while in the New Forest, an area known to be endemic for Lyme disease. When I later developed neurological symptoms and investigations began at the end of June, I reported this tick exposure as part of my medical history.
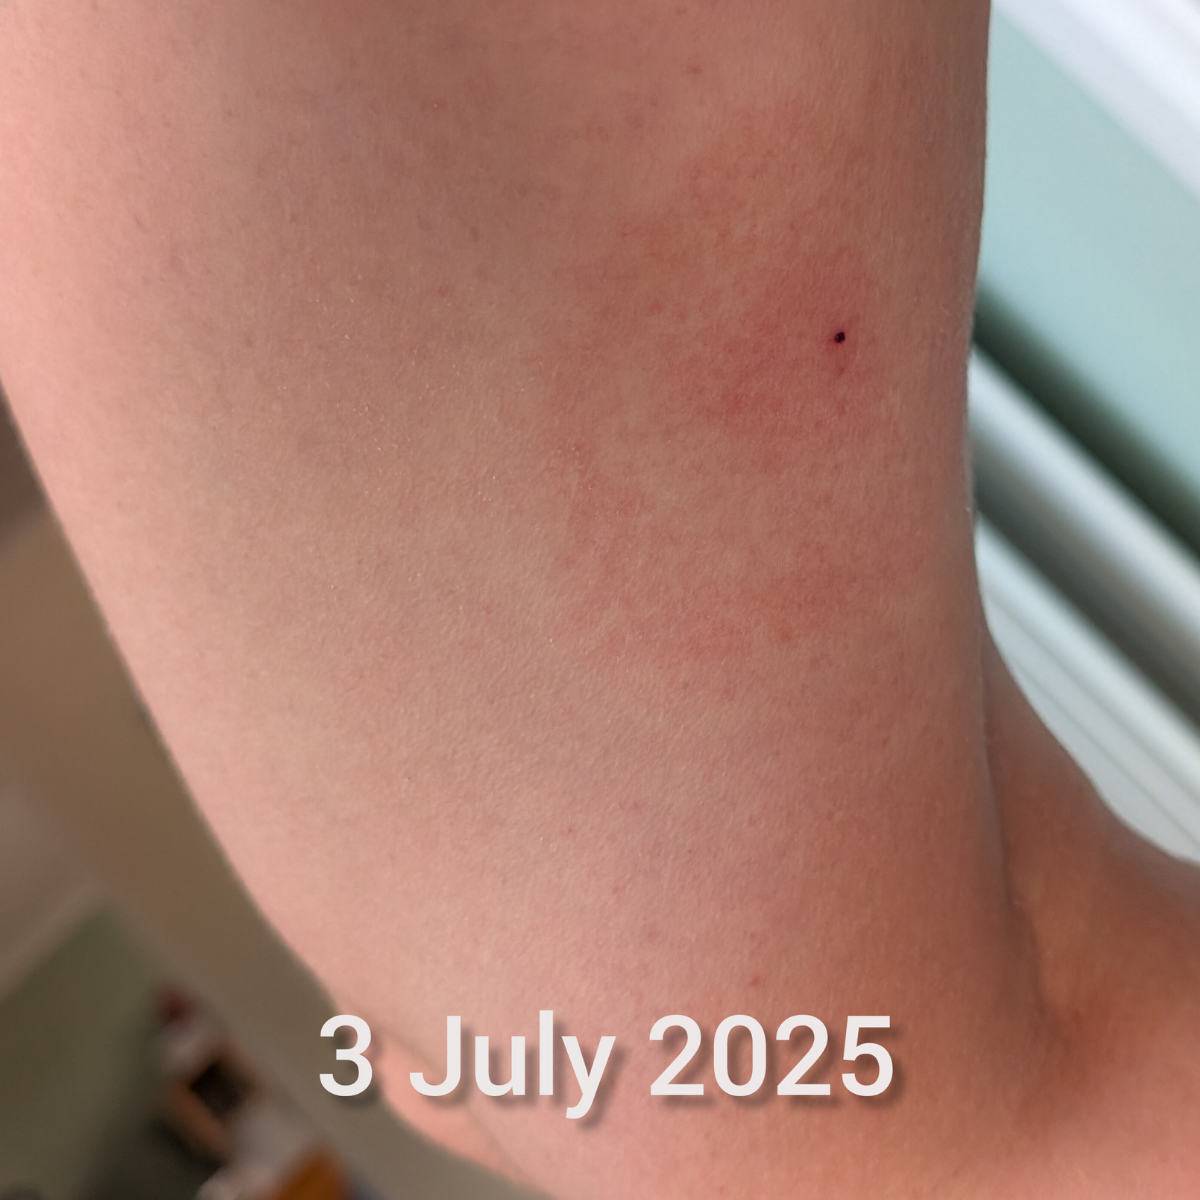
Maja’s 2025 tick bite and EM rash
My first symptoms were neurological in nature. I developed discomfort in my brow area, which I initially thought was a sinus headache; however, sinus medication did not help. I also developed discomfort in my eyes and sought help from a pharmacy and then an optician. I was advised to use eye drops, but they did not help.
A bull’s-eye rash despite a negative test
My symptoms worsened quickly, and at that point I developed severe photophobia, facial tingling and visual disturbances, which led to emergency medical investigations. Given my recent tick bite history, a Lyme ELISA blood test was performed, which was negative. At that stage, the rash had not yet been identified, and the significance of the combination of symptoms was still unclear.
A few days after investigations had started, I happened to notice a rash on the underside of my right thigh. This rash was a classic bull’s-eye erythema migrans rash. As soon as I saw it, I immediately knew what I was dealing with, so I promptly contacted my GP. Given my history and symptoms, I was prescribed a standard dose of doxycycline for Lyme disease.
Self-advocacy and the NICE guideline
My Lyme disease diagnosis was clinical in nature, based on the history of a tick bite, the appearance of the rash and the symptoms I developed. During my later investigations over the year, I had three additional Lyme ELISA tests and one immunoblot, all of which were negative.
Unfortunately, a couple of days after starting the antibiotics I returned to hospital for further investigations due to worsening symptoms. There, I advocated for my antibiotics to be adjusted to a higher dose as per NICE guidelines for potential CNS involvement.
The attending doctor consulted a senior clinician, and it was agreed that I should take the dose required to cover possible CNS involvement. The only abnormal laboratory finding at that stage was a low lymphocyte count, which I was told was likely due to my body fighting some form of infection. I was also tested for COVID-19, which was negative.
Despite my clinically diagnosed EM rash, I was told by some clinicians that they did not believe my symptoms were due to Lyme disease. I found this confusing, particularly as I had understood that the EM rash was considered diagnostic of Lyme disease under NICE guidance.
The following day my symptoms worsened again and I underwent a lumbar puncture during a SDEC assessment. At the time, I understood that the cerebrospinal fluid (CSF) sample would be sent for specialised neurological Lyme analysis, given my neurological symptoms and concerns about possible neuroborreliosis. CSF being sent for neurological Lyme testing was also documented in my discharge letter.
New complications
Following antibiotic treatment, I initially experienced significant improvement, which gave me hope that we were moving in the right direction. However, over time, my symptoms continued to evolve and new problems developed.
I began experiencing chest pains and palpitations, which resulted in several visits to A&E. Given my medical history and previous Lyme disease diagnosis, there was at one point a concern raised about the possibility of Lyme carditis. However, the investigations performed, including ECGs, blood tests, chest X-ray and cardiac ultrasound, did not identify findings that supported this diagnosis.
As I noticed a relationship between my symptoms and posture, I began researching and considering whether autonomic dysfunction, including POTS, could explain some of my symptoms.
Conflicting medical advice
As part of my investigations, I underwent an MRI brain scan in August 2025. This was reported as normal apart from an unrelated incidental finding. However, this imaging was performed before some of my most severe neurological symptoms developed, including cranial nerve symptoms. My concern has been that later assessments relied on investigations that did not necessarily capture the full evolution of my illness.
During this time, I also managed to secure a second round of antibiotics as per NICE guidelines for potentially failed treatment. The dose was once again adjusted to cover potential CNS involvement during one of my A&E attendances. I have always kept to NICE guidelines during my advocacy, so this was not an unreasonable request and, as such, it was granted.
Later, towards the end of August/beginning of September 2025, I developed sudden-onset swallowing difficulties, which resulted in hospital admission and further investigations. During this admission, I was told that I did not have Lyme neuroborreliosis. At the time, I assumed this conclusion was based on the CSF results from the lumbar puncture that had previously been performed.
On admission, I was also advised to discontinue my second antibiotic treatment, only one week into the course. I followed this advice, but reflecting on it afterwards, I wish I had not stopped the antibiotics before completing the full course.
Incomplete testing
I later discovered that the CSF sample had not been sent for specialised Lyme analysis and that I had not actually undergone the testing I believed had informed the conclusion of neuroborreliosis being ruled out. This added significant uncertainty when trying to understand whether neurological Lyme disease had been adequately assessed.
Clinicians also relied upon MRI results which had been performed before my most severe symptoms developed, such as dysphagia and double vision. This became particularly important because negative blood results subsequently appeared to carry significant weight in decisions about my diagnosis, despite my existing clinical diagnosis of Lyme disease as per NICE guidelines, based on an EM rash, and despite the fact that specialised CSF Lyme analysis had not been performed.
Later, I learned that published evidence recognises that some patients with neuroborreliosis may not demonstrate blood seroconversion despite evidence of infection being detected through CSF testing.
A POTS diagnosis and more symptoms
Some time after being discharged from hospital, I returned to A&E due to worsening chest pain and palpitations. I asked a clinician whether POTS could be a possibility. I underwent a lying-to-standing assessment, which produced results compatible with POTS.
This was an important moment for me because I felt that, without advocating for myself and explaining the pattern I had noticed, my symptoms may have been dismissed because initial investigations were normal. By that stage, I felt that clinicians were beginning to question whether my symptoms had an organic basis, as I had already been given a possible FND label during my admission for dysphagia.
After this, my symptoms continued to progress. I experienced severe sensations of head and brain pressure, associated with pulsating and whooshing tinnitus. This was particularly severe when lying down and became one of the most distressing symptoms I experienced.
There was a point where I could not tolerate lying down because of the pressure symptoms, but each time I stood up to relieve them, I experienced severe chest pains and palpitations from POTS, which at that stage was not yet treated. This was one of the darkest periods of my illness because I felt trapped between symptoms from different systems, with no clear explanation.
New neurological challenges
As my symptoms continued to progress, I developed binocular double vision. This was assessed by ophthalmology and considered potentially consistent with a mild sixth nerve palsy. I then developed worsening and new sensory symptoms, including paraesthesia and nerve pain radiating from my spine to my limbs, which was particularly severe at night. The pain was unlike anything I had experienced before and involved many nights of suffering and sleeplessness.
At one point, the pain attack was so severe that I was unable to move due to the pain shooting across multiple areas of my back, and I was taken to A&E by ambulance.
Multi-systemic symptoms mount
Shortly after this episode, I developed new bladder symptoms involving urinary frequency and urgency. My autonomic symptoms also evolved further and involved air hunger, blood pooling, livedo rash on my legs and my toes turning purple/blue.
During this time, I also developed severe scalp pain which, together with my other symptoms, led to further investigations including assessment for possible vasculitis. The scalp pain was also considered potentially related to trigeminal nerve involvement, given the nature and distribution of the symptoms. I was prescribed carbamazepine to help manage the symptoms.
I underwent a PET-CT scan, which did not demonstrate vasculitis but did show bilateral reactive lymph nodes (non-malignant). By that point I had lost 10kg of weight.
Neurological Lyme disease confirmed
I kept being referred to neurology by multiple consultants and I was finally offered a neurology appointment in December. During this appointment I was told that I do have neurological Lyme disease, likely affecting the central nervous system and my previous Lyme tests were false negatives. My symptoms were mapped to possible cranial nerve involvement, including the abducens, trigeminal and glossopharyngeal nerves and to possible autonomic nervous system involvement.
I was told that there appeared to have been an injury to my nervous system and that my symptoms represented the consequences of that injury, with some symptoms potentially not fully recovering. I was also told that further antibiotics were not indicated, but that a referral would be made to Infectious Diseases. I felt a huge relief as I was finally being heard and my symptoms validated with what I felt was a clear diagnosis.
More diagnostic uncertainty
Unfortunately, the referral to Infectious Diseases never materialised, so I sought a private Infectious Diseases appointment. This only created uncertainty surrounding my illness, as during the appointment the Infectious Diseases consultant acknowledged that my EM rash was compatible with Lyme disease but concluded that there remained diagnostic uncertainty due to the serology results and the timeline of my symptoms.
We also discussed the possibility that early antibiotic treatment may have affected the initial CSF results. The Infectious Diseases consultant felt that my neurological symptoms developed too soon to be compatible with neurological Lyme disease. However, I later learned that clinical literature does recognise that early neurological symptoms can sometimes develop within days or a week after infection. Although this may not represent the most typical presentation, such occurrences have been identified as consistent with neurological Lyme disease.
Given this uncertainty, the consultant recommended further investigations, including Lyme Immunoblot testing, which he kindly arranged for me through the NHS.
A confusing FND label
Shortly afterwards, I had a follow-up neurology appointment. I was told that, due to the negative tests, they were going to diagnose me with Functional Neurological Disorder (FND) and that I would be discharged from neurology.
This diagnosis felt very abrupt, unclear and confusing. It also felt contradictory to the previous rationale provided by the same neurology doctor and did not explain objective findings such as POTS or the ophthalmology measurements related to my double vision.
I raised my concerns with PALS, which resulted in a review by the neurology lead clinician and subsequently a referral for a second opinion at a different NHS trust, which I am still awaiting.
The importance of patient advocacy
One of the hardest parts of this journey has been dealing with the medical system on top of the severe, life-limiting symptoms. During this process, I contacted PALS multiple times to seek clarification about my care and the reasoning behind decisions. Although my concerns were acknowledged, the questions I raised were not directly answered by the clinicians involved. This eventually led to a formal complaint, for which I am still awaiting a response.
This experience has taught me how important it is for patients to advocate for themselves. Advocacy does not mean rejecting medical opinions or believing you have all the answers. For me, it has meant asking questions, requesting explanations, reviewing my medical records and ensuring that the timeline of my illness is properly understood.
Connecting the dots alone
Living with complex symptoms is difficult enough. Trying to navigate uncertainty, multiple specialties and changing interpretations of your illness adds another layer of challenge.
Patients should not have to become the person connecting the dots between appointments, investigations and different specialists, but unfortunately this is often what happens when conditions do not fit neatly into one pathway.
My hope in sharing my story is to highlight the importance of listening to patients, communicating clearly when opinions change, and ensuring that people with complex illnesses feel supported rather than left trying to understand their own diagnosis alone.
It has also been heartbreaking to learn through support groups that many patients feel dismissed or gaslighted, even when their clinical history and symptoms raise concerns for Lyme disease. Reflecting on my own experience, I often think about how different my journey could have been if I had not found the EM rash. Without that objective clinical finding, my diagnosis may have been even more difficult to establish, given that all of my subsequent Lyme serology tests were negative.
Finding that rash became a crucial moment in my journey because it provided an important piece of clinical evidence that helped explain the symptoms I was experiencing. It has made me appreciate how challenging it can be for patients whose presentations are less clear-cut and who are trying to navigate uncertainty without a similar piece of evidence.
An ongoing search for answers
I truly hope that the future brings more research and clearer pathways for diagnosis, treatment and ongoing support for patients who do not recover in the conventional way.
Today, just over a year since my journey began, I am still battling debilitating symptoms related to autonomic dysfunction, headaches with eye discomfort, double vision, visual disturbances, widespread nerve pain and fatigue. I am still searching for answers, but this journey has shown me the importance of persistence, self-advocacy and being an active participant in my own healthcare.
Life-changing illness
Before becoming ill, I lived a busy and active life. I worked, ran a successful small animal boarding business with many returning clients, trained regularly in kickboxing, enjoyed caving and spent much of my free time outdoors with my horses and goats. Caring for my animals was never simply a responsibility – it was a huge part of who I am and something that brought me immense happiness.
Over the following months, that life changed completely. During the early stages of my illness, the severe photophobia became so overwhelming that I spent almost three weeks sitting in a dark room because I simply could not tolerate light. My brother travelled from another country to support us during this period because I was unable to manage everyday life independently.
My illness also affected my work in a way I had never imagined. When I became acutely unwell, it was the middle of the busy summer season. We had no choice but to cancel numerous bookings at very short notice because I was simply too ill to provide the standard of care that people and their pets deserved.
As my symptoms progressed, I became unable to drive – initially because of the severe photophobia and later because of persistent binocular double vision, headaches and eye pain. Losing that independence had a huge impact on my daily life.
The impact on family
The illness affected my entire family. My fiancé’s mother stepped in to help care for both our animals and my son because there were many things I simply could not do. Looking back, I honestly do not know how we would have managed without her support.
One memory has stayed with me more than any other. My son was celebrating his ninth birthday with his friends while I sat alone in another part of the house crying my eyes out because I was overwhelmed by the severity of my symptoms, the uncertainty surrounding what was happening to me and the inability to join in with the celebrations. As a parent, that is a memory that stays with you.
The illness also placed strain on my relationship with my fiancé. Watching someone you love become seriously unwell while no one can provide clear answers is incredibly difficult. There were times when I even found myself questioning my own sanity as different clinicians reached different conclusions about what was happening to me.
Some symptoms changed everyday family life in ways I never expected. The severe burning pain and allodynia mean that even gentle touch can sometimes be painful. As a mother, that has been particularly difficult because there have been times when my son has simply wanted a cuddle, and despite desperately wanting to meet this need, my body could not tolerate being touched.
Clinical support brings relief
Despite the challenges, I was fortunate to have healthcare professionals who made a genuine difference. My GP practice supported me throughout this journey, with one GP in particular taking the time to listen, remain involved in my care and help me navigate an increasingly complex medical picture.
Starting beta-blockers for my POTS and orthostatic hypertension became one of the biggest turning points in my recovery. Before treatment, the chest pain, palpitations and overwhelming feeling of becoming unwell whenever I stood upright had left me with poor quality of life.
The medication did not resolve all of my health problems, but it transformed one of the most disabling aspects of my illness, allowing me to remain upright again without constantly feeling overwhelmed by the symptoms. Amitriptyline has also improved my sleep and reduced some of the neuropathic symptoms, making daily life more manageable.
I am also incredibly grateful to the consultants who recognised how complex my case has been and approached it with empathy and openness. In particular, my ophthalmology consultant has consistently taken my symptoms seriously and continued to review me throughout my illness. Having clinicians who acknowledged uncertainty, listened and treated me as a partner in my care made an enormous difference during a time when so much else felt uncertain.
Moving forward
Today, I am in a better place than I was at the beginning of this journey. Although I continue to experience many daily symptoms and am still far from the physically active life I enjoyed before becoming ill, through careful pacing and learning to prioritise my energy I have gradually regained the ability to carry out many basic daily tasks, care for my animals again and slowly rebuild parts of my life.
Emotionally, I feel stronger than I did during those darkest months. However, I still carry the burden of everything that has happened over the past year. The uncertainty surrounding my diagnosis, the changing medical opinions and the long search for answers have left an impact that extends far beyond my physical symptoms.
I never wanted to become someone who reads clinical papers, studies NICE guidelines, requests Subject Access Requests or learns to interpret medical investigations. I wanted to be working, training in kickboxing, exploring caves, caring for my animals and making memories with my family.
Advocating for myself was never about challenging doctors. It became necessary because, when you are living with severe symptoms and profound uncertainty, asking questions is sometimes the only way to continue moving forward.
Sharing our stories matters
I recognise that I have been fortunate to have a scientific background, which gave me tools that helped me navigate an incredibly complex medical journey. It allowed me to read scientific literature, understand clinical guidelines, critically review my medical records and write factual, evidence-based correspondence through PALS and the NHS complaints process.
Even with those skills, I often found the system difficult to navigate. It has made me think about how much harder this experience must be for patients who do not have the confidence, time or background to do the same. My hope in sharing my story is that it encourages both patients and healthcare professionals to remember that behind every scan, every blood test and every clinic letter is a person, a family and a life that has been profoundly changed.